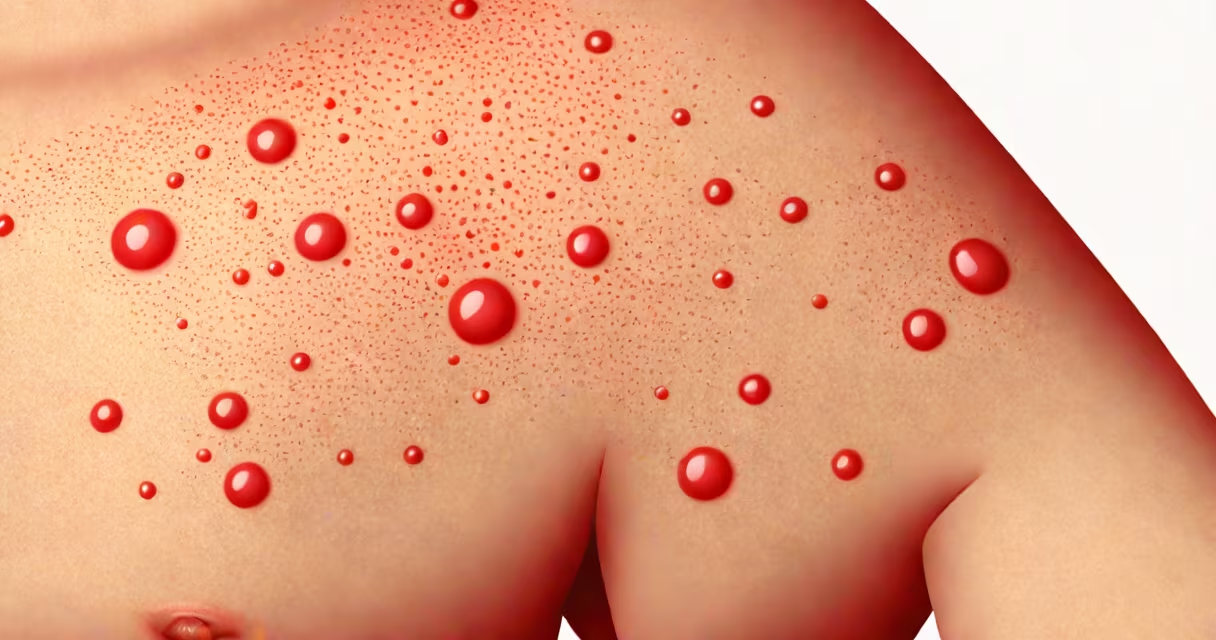
Staph on body describes an infection caused by Staphylococcus aureus bacteria colonizing the skin or entering through a break in the skin barrier. These bacteria are common on human skin and mucous membranes but can cause illness when they invade deeper tissues.
Staphylococcus aureus is a Gram-positive bacterium that lives harmlessly on about 30% of people's skin and nasal passages. When it breaches the skin's protective layer-through cuts, scratches, or insect bites-it can trigger localized infections such as folliculitis, furuncles (boils), or abscesses. In rare cases, it spreads systemically, leading to life-threatening conditions like sepsis or pneumonia.
The Centers for Disease Control and Prevention (CDC) reports that methicillin-resistant S. aureus (MRSA) accounts for about 15% of invasive staph infections in the U.S., with higher rates in healthcare settings. MRSA is resistant to many common antibiotics, making treatment more complex.
Staph on body begins when S. aureus enters the body through a wound, surgical site, or compromised skin. The bacteria multiply rapidly in warm, moist environments-like under bandages or in tight clothing-and release toxins that damage tissue and attract immune cells, resulting in inflammation.
Common entry points include minor injuries such as scrapes, acne lesions, or hair follicle irritation. Once inside, the bacteria form biofilms-protective layers that shield them from both the immune system and antibiotics. This explains why some staph infections persist despite treatment.
A 2021 study published in *The Lancet Infectious Diseases* found that 62% of community-acquired skin abscesses were caused by S. aureus, with 18% being MRSA-positive. Most cases resolve with drainage and oral antibiotics, but failure to treat increases risk of systemic spread.
Staph on body manifests in several distinct forms, each with unique presentation and management:
| Type | Appearance | Location | Treatment |
|---|---|---|---|
| Folliculitis | Red, pus-filled bumps around hair follicles | Arms, legs, scalp | Topical antiseptics, warm compresses |
| Furuncle (Boil) | Painful, deep red lump that drains pus | Neck, face, buttocks | Incision and drainage; oral antibiotics if severe |
| Carbuncle | Cluster of interconnected boils, often with fever | Back of neck, shoulders | Hospitalization may be needed; IV antibiotics |
| Impetigo | Crusted, honey-colored sores; highly contagious | Face, hands | Topical mupirocin; oral antibiotics for widespread cases |
One non-obvious fact: staph infections can mimic other skin conditions. A 2019 case series in *JAMA Dermatology* documented five patients initially diagnosed with eczema or psoriasis who later tested positive for S. aureus after biopsy. Misdiagnosis delays effective treatment and increases transmission risk.
Staph on body thrives in crowded, warm environments. Outbreaks are common in gyms, locker rooms, and daycare centers due to shared equipment and close contact. The bacteria survive on surfaces like gym mats, shower floors, and towels for up to 24 hours.
High-risk groups include athletes using shared gear, hospital patients with catheters or wounds, and individuals with weakened immunity. A 2020 CDC report showed that 41% of MRSA skin infections in adults occurred in otherwise healthy individuals with no known risk factors-underscoring that anyone can contract staph on body.
I once treated a patient with recurrent boils on his upper back. He wore a backpack daily and kept it in a damp corner of his apartment. After switching to a dry, ventilated bag and using antiseptic wipes on the shoulder straps, his outbreaks ceased within six weeks. This illustrates how environmental hygiene plays a direct role in preventing staph on body.
Staph on body is often mistaken for fungal infections, especially athlete's foot or ringworm. Both can cause red, scaly patches, but fungal rashes typically spread outward in circular patterns and respond to antifungals-not antibiotics. Misidentifying staph as fungus leads to ineffective treatment and prolonged discomfort.
Another misconception: staph only affects unclean people. S. aureus is part of normal skin flora. Healthy individuals carry it asymptomatically. The presence of bacteria doesn't equal disease. Infection occurs only when the balance shifts-due to injury, immune suppression, or antibiotic disruption of competing microbes.
Also, not all staph infections require antibiotics. Mild folliculitis often resolves with warm compresses and cleanliness. Overprescribing antibiotics fuels resistance. The American Academy of Dermatology advises against using oral antibiotics for uncomplicated skin infections unless signs of spreading or systemic illness appear.
Seek care if a skin lesion grows larger than 1 cm, becomes increasingly painful, or develops red streaks radiating from the site. Fever above 100.4°F (38°C), chills, or swelling in nearby lymph nodes indicate possible systemic spread.
For suspected MRSA, doctors perform swab cultures. If positive, treatment includes clindamycin or trimethoprim-sulfamethoxazole. Hospitalized patients may receive vancomycin intravenously. Early intervention reduces complications.
Prevention involves daily handwashing, avoiding sharing personal items like razors or towels, and cleaning high-touch surfaces. Wound care is critical: clean cuts with soap and water, cover with sterile gauze, and monitor for redness or discharge.