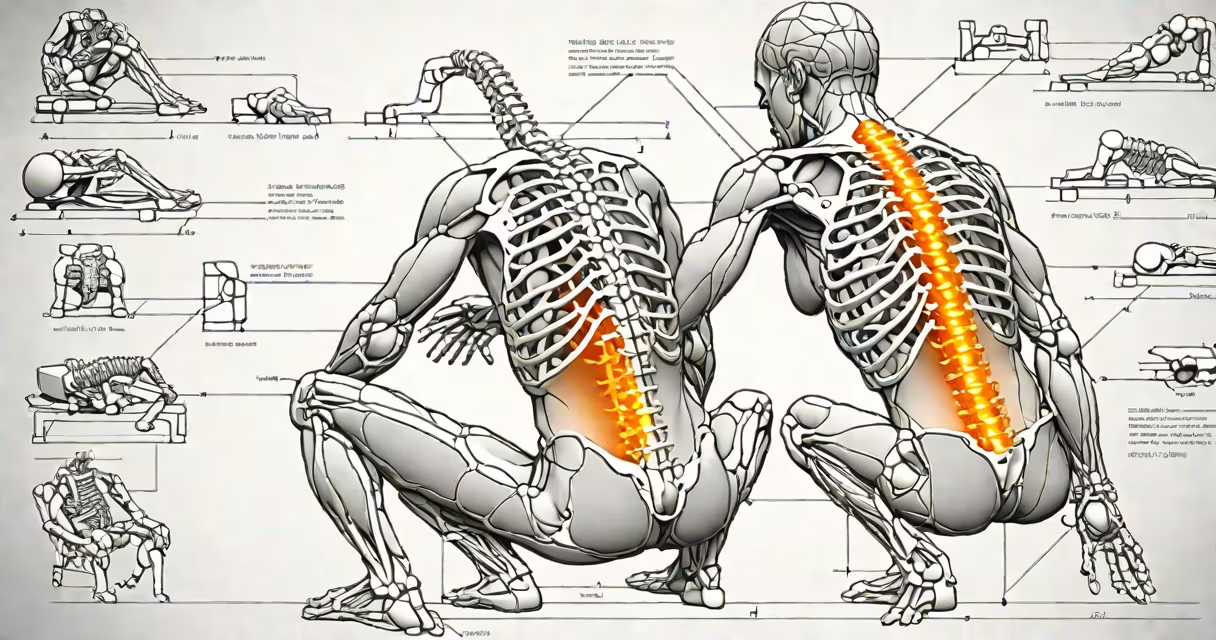
Bottom vertebrae pain describes localized discomfort in the lower back, specifically around the lumbar spine's five vertebrae (L1-L5), often due to mechanical strain, disc degeneration, or nerve compression. This pain may radiate into the hips, buttocks, or legs depending on the underlying cause.
The lumbar spine bears most of the body's weight during standing, walking, and lifting. When the discs between vertebrae lose hydration or develop tears, they can bulge or herniate, pressing on nearby nerves. This leads to sharp, shooting, or dull aching sensations in the lower back. Pain typically worsens with bending, twisting, or prolonged sitting.
According to the American Academy of Orthopaedic Surgeons (AAOS), 80% of adults experience low back pain at some point in life, with the majority resolving within six weeks without surgery. However, persistent bottom vertebrae pain lasting beyond four weeks warrants medical evaluation to rule out structural or neurological issues.
Pain originates when spinal structures fail to absorb stress properly. The intervertebral discs act as shock absorbers between vertebrae. As they age or sustain trauma, their outer layer (annulus fibrosus) can weaken, allowing the inner gel-like nucleus pulposus to protrude. This condition-disc herniation-can compress the sciatic nerve root, causing radiating pain down the leg.
Nerve roots exiting the spinal cord at L4-L5 and L5-S1 levels control sensation and movement in the lower limbs. Compression here results in symptoms like numbness, tingling, or muscle weakness. For example, a herniated L5 disc may cause foot drop-a condition where the foot cannot lift properly during walking.
A 2021 study published in *Spine Journal* found that individuals with sedentary jobs had a 3.2 times higher risk of developing chronic lower back pain compared to those with physically active roles. Prolonged sitting reduces blood flow to the discs, accelerating degeneration.
Bottom vertebrae pain stems from several distinct conditions. The most frequent include:
| Type | Key Features | Typical Triggers |
|---|---|---|
| Disc herniation | Pain radiates down one leg; may involve numbness or weakness | Lifting heavy objects, sudden twist |
| Spinal stenosis | Leg pain worsens with walking; improves when leaning forward | Age-related narrowing of spinal canal |
| Muscle strain | Localized soreness; improves with rest and heat | Overexertion, poor posture |
| Sacroiliac joint dysfunction | Pain near the hip bone; may feel like a deep ache | Pregnancy, repetitive twisting motions |
One non-obvious distinction: sciatica is not a diagnosis but a symptom. It refers to pain along the sciatic nerve path, which runs from the lower back through the buttock and down the back of each leg. Not all bottom vertebrae pain involves sciatica-only cases where nerve irritation occurs.
I once treated a 42-year-old office worker whose bottom vertebrae pain began after a weekend of moving furniture. He reported sharp pain radiating from his left lower back into his thigh and calf. MRI confirmed a left-sided L4-L5 disc herniation compressing the L5 nerve root. After six weeks of physical therapy and anti-inflammatory medication, his symptoms resolved completely.
Bottom vertebrae pain is often mistaken for general back stiffness or fatigue. But red flags signal a need for prompt evaluation. These include:
These signs may indicate cauda equina syndrome-a rare but serious condition requiring emergency surgery. The National Institute of Neurological Disorders and Stroke (NINDS) reports that delayed treatment increases the risk of permanent paralysis.
Doctors begin with a physical exam assessing range of motion, reflexes, and sensory changes. Imaging such as MRI or CT scans confirms structural abnormalities. Nerve conduction studies may be used if peripheral nerve involvement is suspected.
Treatment depends on severity. Most cases improve with conservative care: activity modification, targeted exercises, and NSAIDs. A 2020 review in *The Lancet* concluded that exercise programs tailored to core strength and flexibility reduced recurrence rates by 45% over 12 months.
For persistent cases, interventions like epidural steroid injections or minimally invasive procedures may be recommended. Surgery is reserved for severe nerve compression or failure of nonoperative treatment after three months.
Bottom vertebrae pain is not a single condition but a symptom cluster rooted in biomechanics, aging, and lifestyle. Recognizing early warning signs and seeking timely care prevents long-term disability. If pain lasts longer than four weeks or includes neurological deficits, consult a spine specialist.