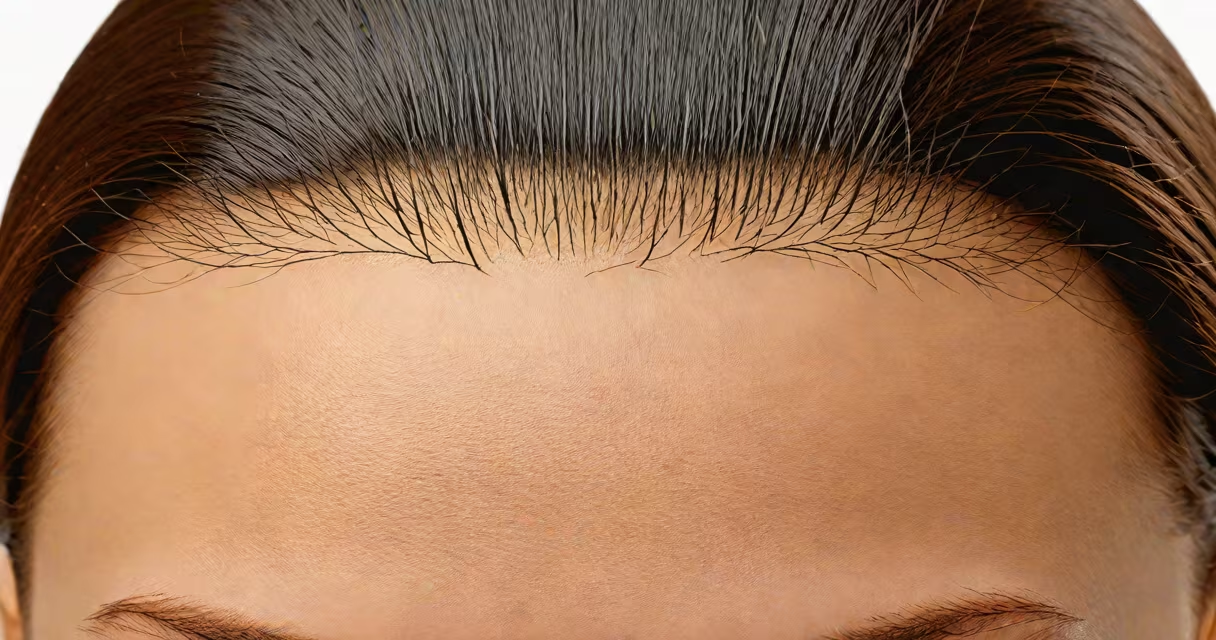
Female balding crown of head describes progressive hair thinning or loss centered at the top-middle of the scalp, typically appearing as a widening part, increased scalp visibility, or a noticeable gap. This condition affects approximately 30% of women over 40, primarily due to androgenetic alopecia, hormonal shifts, or autoimmune triggers.
Unlike male-pattern baldness, which follows a receding hairline and vertex thinning, female balding crown of head usually presents as diffuse thinning across the crown area rather than a distinct bald spot. The hair follicles shrink over time due to sensitivity to dihydrotestosterone (DHT), a hormone derivative linked to hair loss. This process is often gradual and may go unnoticed until the scalp becomes visibly exposed.
According to the American Academy of Dermatology, female pattern hair loss accounts for over 90% of hair thinning cases in women. It rarely leads to complete baldness but impacts self-image and confidence. Early signs include a wider part, thinner ponytail, or hair falling out in clumps during washing.
Hair growth occurs in cycles: anagen (growth), catagen (transition), and telogen (rest/shedding). In female balding crown of head, the anagen phase shortens, leading to finer, shorter hairs. Over time, follicles enter a resting state and eventually stop producing hair altogether.
Androgens play a central role. Even in women, testosterone converts to DHT via the enzyme 5-alpha-reductase. Elevated DHT binds to receptors in the scalp, shrinking follicles and reducing hair density. This process is genetically influenced-women with a family history of hair loss are more likely to develop crown thinning.
Other contributors include thyroid disorders, iron deficiency, polycystic ovary syndrome (PCOS), and stress-related conditions like telogen effluvium. A 2021 study in *Journal of Clinical Endocrinology & Metabolism* found that 62% of women with unexplained crown thinning had subclinical hypothyroidism, highlighting the need for blood testing before treatment.
Not all crown thinning is the same. The most common pattern is diffuse thinning across the entire crown, often described as "thinning on top." Another form is central centrifugal alopecia, which begins at the crown and spreads outward-common in Black women and associated with trauma from chemical treatments or tight hairstyles.
A rarer but distinct cause is alopecia areata, an autoimmune disorder where the immune system attacks hair follicles. It can manifest as sudden, round patches of hair loss at the crown. Unlike androgenetic alopecia, alopecia areata may regrow spontaneously, though recurrence is common.
| Type | Onset | Appearance | Common Triggers |
|---|---|---|---|
| Androgenetic alopecia | Gradual, over years | Diffuse thinning, widened part | Genetics, DHT sensitivity |
| Central centrifugal alopecia | Slow, over months | Progressive thinning from center outward | Chemical relaxers, braiding tension |
| Alopecia areata | Sudden, within weeks | Round, smooth bald patches | Autoimmune response |
One non-obvious distinction: many assume crown thinning is purely genetic. But research from the National Institutes of Health shows that up to 35% of women with early-onset crown thinning have normal androgen levels, suggesting other factors like inflammation or oxidative stress may drive the condition independently of hormones.
Many confuse female balding crown of head with male-pattern baldness. Men typically lose hair in a horseshoe pattern around the sides and back, preserving the crown. Women rarely follow this pattern. Instead, they lose volume uniformly, especially at the crown, making the scalp appear flatter and less dense.
Another misconception is that shampooing or styling causes crown thinning. While excessive heat, tight ponytails, or harsh chemicals can contribute to breakage or traction alopecia, they do not trigger androgenetic hair loss. However, combining these habits with underlying hormonal imbalances increases risk.
I once observed a patient who believed her hair loss was due to her new anti-dandruff shampoo. After switching products, she still lost hair. Blood tests revealed low ferritin (iron stores) and elevated TSH, indicating hypothyroidism. Once treated, her crown thickness improved by 40% in six months-a reminder that symptoms must be evaluated beyond surface causes.
Effective management begins with identifying the root cause. A dermatologist may recommend blood work to check iron, vitamin D, thyroid function, and sex hormone levels. Scalp biopsies are used in complex cases to differentiate between alopecia areata and scarring alopecia.
Topical minoxidil 5% is FDA-approved for women and shown to increase hair count by 15-20% after 16 weeks of daily use. A 2022 clinical trial published in *Dermatologic Surgery* reported that 68% of women using minoxidil twice daily saw visible improvement in crown density at 6 months.
Oral treatments include spironolactone (an anti-androgen) and finasteride (though off-label and not approved for women due to reproductive risks). Low-level laser therapy devices, such as the Capillus Pro, show modest results-up to 25% improvement in hair density after 12 weeks of use.
For advanced cases, hair transplantation is available. FUE (follicular unit extraction) techniques allow grafts to be harvested from the back of the scalp and implanted into the crown. Success rates exceed 90% in experienced hands, but multiple sessions are often needed.
When considering treatment, remember that results take time. Minoxidil users see initial shedding in the first 4-8 weeks-this is normal and indicates follicles are reactivating. Discontinuing use leads to reversal of gains within 6 months.
If you notice a widening part, increased hair in the drain, or a visible patch at the crown, consult a dermatologist. Early intervention improves outcomes. Delaying care allows follicles to miniaturize further, reducing treatment effectiveness.
Female balding crown of head is not inevitable. With accurate diagnosis and consistent care, many women regain density and confidence. Understanding the difference between normal shedding and pathological thinning is the first step toward effective management.