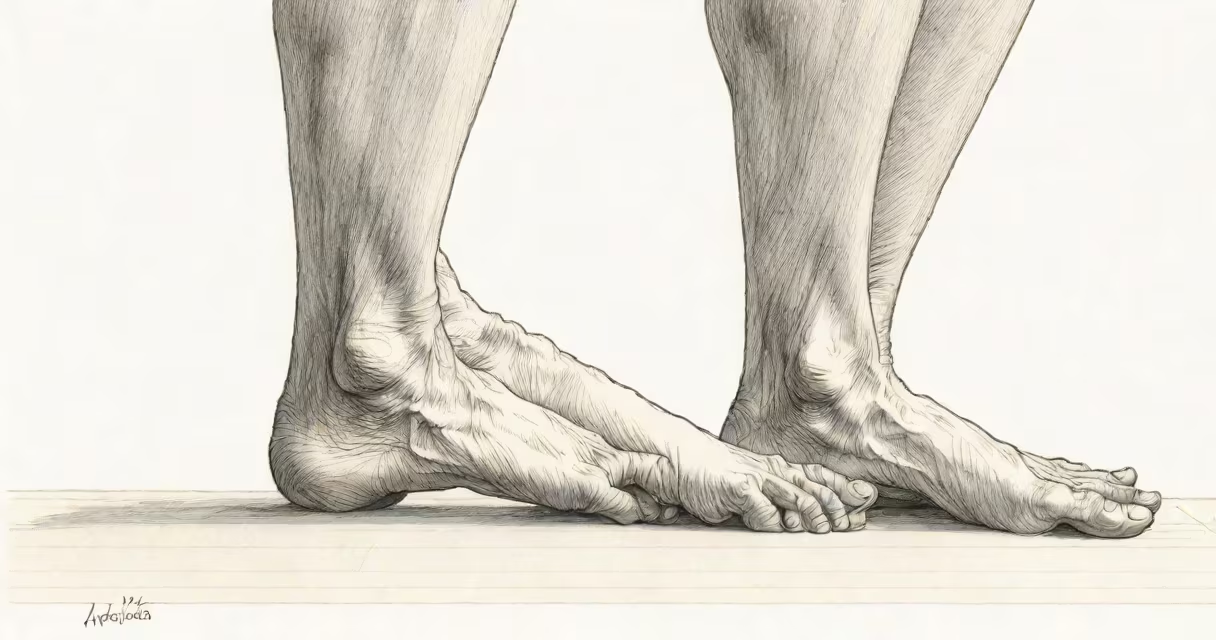
Flat feet, medically known as pes planus, occur when the arches of the feet do not develop properly or collapse over time, causing the entire sole to contact the ground during standing or walking. This condition affects approximately 20% of adults and can result from genetics, injury, aging, or underlying health issues.
Flat feet develop when the ligaments and tendons supporting the foot's arch weaken or stretch. In children, it's common for arches to appear gradually between ages 3 and 6. If arches fail to form by age 6, or if they disappear later in life, the condition may persist into adulthood. The most common cause is inherited foot structure, but acquired flat feet can stem from trauma, obesity, diabetes, or rheumatoid arthritis.
According to the American Academy of Orthopaedic Surgeons (AAOS), flat feet affect about 20% of adults and are often asymptomatic. However, when pain or mobility issues arise, medical evaluation is recommended. The condition is not inherently dangerous, but it can contribute to long-term strain on the lower limbs.
The foot contains 26 bones, 33 joints, and over 100 muscles, tendons, and ligaments. The medial longitudinal arch-the inner side of the foot-is primarily supported by the posterior tibial tendon, which runs along the inside of the ankle. When this tendon becomes inflamed or weakened, it can no longer hold the arch up, leading to overpronation and a flattened appearance.
Overuse, especially in runners or those who stand for long periods, accelerates wear on the arch-supporting structures. A 2021 study published in *Foot & Ankle International* found that individuals with flat feet were 3.2 times more likely to report chronic foot pain compared to those with normal arches. This increased risk stems from altered biomechanics during gait, where the foot rolls inward excessively.
Another factor is weight distribution. Excess body mass increases pressure on the plantar fascia-the thick band of tissue running along the bottom of the foot. Prolonged stress can lead to fasciitis, a painful inflammation that worsens the flattening effect. For example, a 200-pound adult walking 5,000 steps daily places roughly 10 tons of cumulative load on their feet over a year.
Flat feet fall into two categories: flexible and rigid. Flexible flat feet retain some arch when the foot is off the ground-common in children and often harmless. Rigid flat feet show no arch even when the foot is lifted, indicating structural changes such as bone fusion or joint degeneration. Rigid flat feet are less common but more likely to cause pain and require intervention.
| Type | Arch Visibility When Standing | Arch Visibility When Sitting/Toe Lift | Common Causes |
|---|---|---|---|
| Flexible | Visible only when weight is removed | Arch returns | Genetics, childhood development, mild overuse |
| Rigid | No visible arch | No arch return | Arthritis, trauma, congenital deformity |
A common misconception is that flat feet always cause pain. The reality, confirmed by the Mayo Clinic, is that many people with flat feet live without discomfort. Pain only arises when biomechanical imbalance leads to secondary issues-such as shin splints, knee pain, or hip misalignment-due to improper force transmission through the kinetic chain.
Another myth is that flat feet prevent participation in sports. In fact, many elite athletes have flat feet. NBA player Chris Paul has documented flat feet and uses custom orthotics. His performance remains unaffected because proper footwear and support compensate for the lack of arch height.
Pain in the arch, heel, or ankle during or after activity is a red flag. So is difficulty walking on uneven surfaces or persistent swelling. The American Podiatric Medical Association (APMA) recommends seeing a podiatrist if symptoms interfere with daily function or progress over time.
I once observed a patient with undiagnosed posterior tibial tendon dysfunction. He had worn out multiple pairs of shoes due to excessive inward rolling. After a physical exam and MRI, we discovered tendon tearing. He was fitted with a custom orthotic and began physical therapy. Within six weeks, his gait improved.
Diagnosis involves a combination of visual assessment, gait analysis, and imaging. A simple "wet footprint test" can give initial insight: wet your foot and step on paper. A full print indicates flat feet; a narrow print suggests a higher arch.
Most cases of flat feet don't require treatment. When symptoms emerge, conservative measures include supportive footwear, over-the-counter orthotics, and targeted exercises. The APMA recommends strengthening the intrinsic foot muscles through towel scrunches, toe curls, and heel raises.
For severe cases, prescription orthotics or surgical correction may be necessary. Surgery is rare and reserved for patients with significant pain, joint damage, or failure of non-surgical care. Procedures like subtalar arthrodesis or tendon transfer aim to restore stability and correct alignment.
One non-obvious fact: flat feet can improve with consistent exercise. A 2019 randomized trial in *The Journal of Orthopaedic & Sports Physical Therapy* showed that participants who performed daily foot-strengthening routines for 12 weeks reported a 40% reduction in pain and improved arch height on imaging.
Understanding why you are flat-footed begins with recognizing that it's not a disease but a variation in foot structure. Many people live symptom-free. But when pain emerges, addressing posture, footwear, and muscle strength can restore comfort and function.